
MDCAT · Biology (PMDC curriculum) · Unit 13: Respiration
MDCAT Biology Unit 13: Respiration, study guide with practice MCQs
Need more than one subject? All-notes pass: unlimited downloads of every note for a year: unlimited downloads of every note on the site, PKR 999 a year. All packs and courses.

Opens inside this page. Prefer your own PDF app? Open the PDF.
Check yourself
5 quick questions on MDCAT Biology
Tap an answer to see if you are right, and why. Free, no sign-up.
Start the free testWas this note useful?
Full text of MDCAT Biology Unit 13: Respiration, study guide with practice MCQs
What MDCAT asks
This unit covers the human respiratory tract and alveoli, the mechanics of breathing and lung volumes, the carriage of oxygen and carbon dioxide in the blood (haemoglobin, the dissociation curve, the Bohr effect, hydrogencarbonate ions and the chloride shift) and the common respiratory disorders, including the effects of smoking. Its two subtopics carry equal weight and together make up about 2.7% of the Biology paper, so expect 2 or 3 of the 81 Biology questions from here, usually one on breathing mechanics or a lung-volume calculation and one on gas transport or a disorder.
B13.1 Respiratory system and breathing
B13.1.1 Describe the human respiratory tract and alveoli
Air follows one fixed route: nostrils → nasal cavity → pharynx → larynx → trachea → bronchi → bronchioles → alveolar ducts → alveoli. Everything up to the terminal bronchioles is the conducting part, which cleans, warms and moistens the air but exchanges no gases; the respiratory bronchioles, alveolar ducts and alveoli are the respiratory part.
- Nasal cavity: hairs trap particles; the mucus-coated, blood-rich lining warms, moistens and filters the air.
- Pharynx: shared by air and food; during swallowing the epiglottis covers the glottis so food goes down the oesophagus, not the trachea.
- Larynx (voice box): a box of cartilage holding the vocal cords.
- Trachea: held open by C-shaped rings of hyaline cartilage, the open side of each C facing the oesophagus. Lined by ciliated pseudostratified columnar epithelium with goblet cells.
- Bronchi: one primary bronchus per lung, branching further, with plates of cartilage and the same ciliated lining.
- Bronchioles: under 1 mm wide, with no cartilage; walls of smooth muscle that can narrow (asthma) or widen (adrenaline).
- Alveoli: roughly 300 million tiny sacs with a total surface of about 50 to 100 m2.
The right lung has three lobes and the left two. Each lung sits in a pleural sac: the visceral pleura covers the lung, the parietal pleura lines the chest wall, and the film of pleural fluid between them lubricates the surfaces and, by surface tension, holds the lung to the chest wall, so the lungs, which have no muscle of their own, follow every movement of the ribs and diaphragm. In the airways, goblet-cell mucus traps dust and microbes and the cilia sweep it up to the pharynx to be swallowed (the mucociliary escalator).
Alveolar features for diffusion:
- Thin wall: one layer of squamous epithelium against one layer of capillary endothelium, a barrier under 1 micrometre thick.
- Moist lining: gases dissolve before diffusing; surfactant in the film lowers surface tension so the alveoli do not collapse on expiration.
- Huge total surface area from the sheer number of alveoli.
- Dense capillary network and constant ventilation keep the concentration gradients steep.
Gases cross the alveolar wall by simple diffusion only, down partial-pressure gradients. Inspired air is about 21% oxygen and 0.04% carbon dioxide; expired air about 16% and 4%.
B13.1.2 Explain the mechanism of breathing and lung volumes
Breathing moves air because the volume of the thorax changes: gas pressure falls when volume rises and rises when volume falls. The lungs contain no skeletal muscle; the diaphragm (a dome-shaped sheet below the lungs) and the intercostal muscles between the ribs do the work.
Inspiration (active):
- The diaphragm contracts and its dome flattens, lengthening the thorax from top to bottom.
- The external intercostal muscles contract, swinging the ribs up and out, widening the thorax.
- Thoracic and lung volume increase, alveolar pressure falls about 1 mmHg below atmospheric, and air flows in until the pressures are equal.
Quiet expiration (passive): the diaphragm relaxes and domes upwards, the external intercostals relax so the ribs drop down and in, and the stretched elastic tissue of the lungs recoils. Volume falls, alveolar pressure rises about 1 mmHg above atmospheric, and air is pushed out.
Forced expiration (active): blowing out hard or coughing uses the internal intercostal muscles, which pull the ribs down and in, and the abdominal muscles, which push the diaphragm higher. Pleural pressure stays slightly below atmospheric throughout, keeping the lungs partly inflated even after expiration.
Control of breathing. The rhythm is set by the respiratory centre in the medulla oblongata. Chemoreceptors in the medulla respond to a rise in carbon dioxide through the hydrogen ions it produces; those in the carotid and aortic bodies also respond to a large fall in oxygen. A rise in blood carbon dioxide is the main stimulus that speeds and deepens breathing; a fall in oxygen matters only when severe. A resting adult breathes roughly 12 to 20 times a minute.
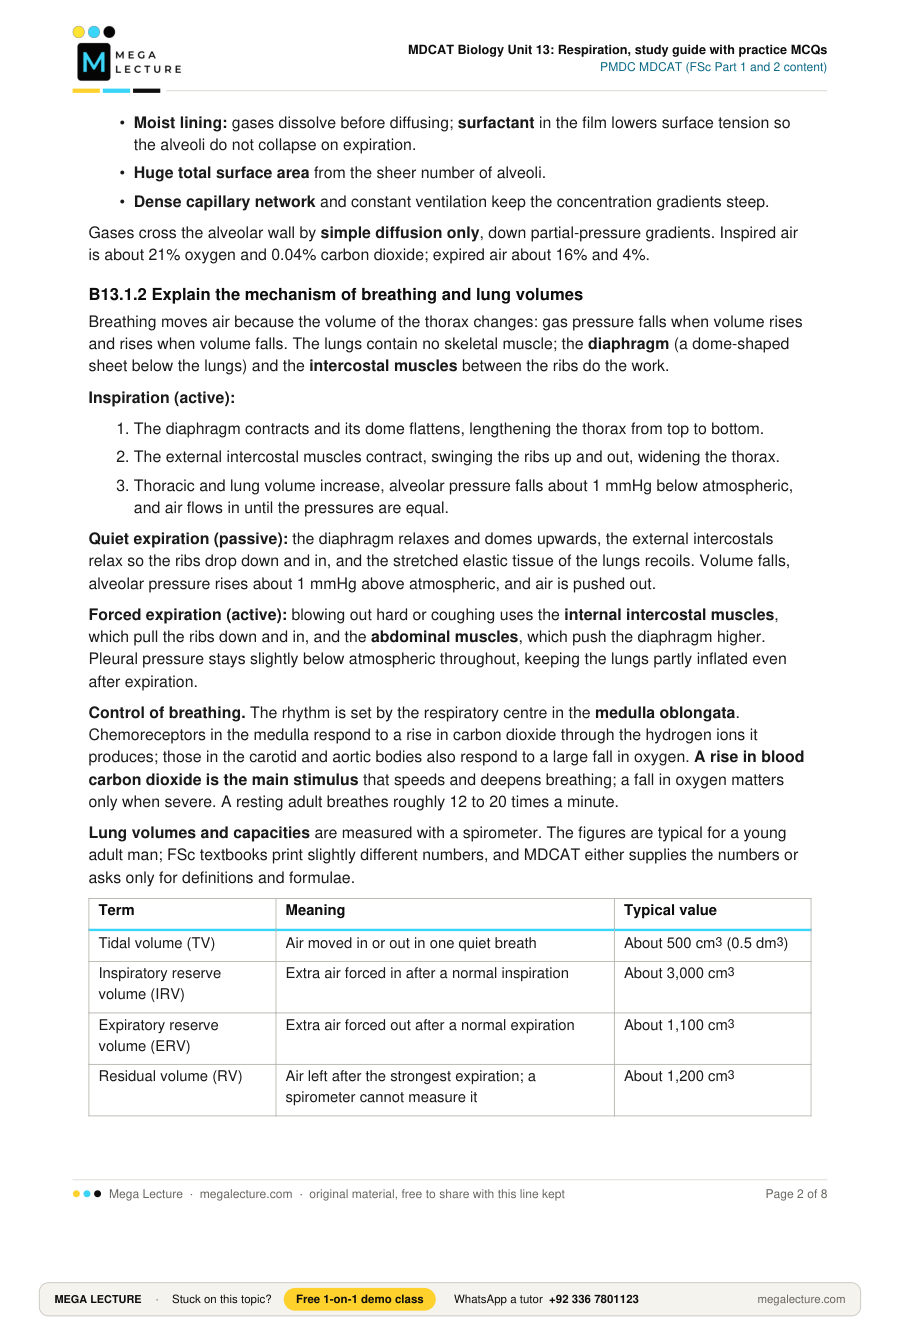
Lung volumes and capacities are measured with a spirometer. The figures are typical for a young adult man; FSc textbooks print slightly different numbers, and MDCAT either supplies the numbers or asks only for definitions and formulae.
| Term | Meaning | Typical value |
|---|---|---|
| Tidal volume (TV) | Air moved in or out in one quiet breath | About 500 cm3 (0.5 dm3) |
| Inspiratory reserve volume (IRV) | Extra air forced in after a normal inspiration | About 3,000 cm3 |
| Expiratory reserve volume (ERV) | Extra air forced out after a normal expiration | About 1,100 cm3 |
| Residual volume (RV) | Air left after the strongest expiration; a spirometer cannot measure it | About 1,200 cm3 |
| Vital capacity (VC) | TV + IRV + ERV: the most air moved in one breath | About 4,500 to 4,800 cm3 |
| Total lung capacity (TLC) | VC + RV | About 5,800 to 6,000 cm3 |
| Anatomical dead space | Air in the conducting airways that never reaches the alveoli | About 150 cm3 |
| Minute volume | TV × breathing rate | About 6,000 to 7,500 cm3 per minute |
Because about 150 cm3 of each breath only fills the dead space, alveolar ventilation = (TV minus dead space) × rate, so deep slow breathing ventilates the alveoli better than rapid shallow breathing at the same minute volume.
MDCAT trap: the lungs do not expand because air rushes in. Students write "air enters the lungs, so the lungs expand and the chest rises". The cause and effect are the other way round, and examiners test exactly this order. The muscles act first: the diaphragm flattens and the external intercostals lift the ribs; that enlarges the thorax, the lungs are pulled outward with it, alveolar pressure drops below atmospheric, and only then does air flow in. Three rules follow. Inspiration is always active and quiet expiration passive; only forced expiration uses the internal intercostals and abdominal muscles. The lungs have no skeletal muscle, so "the lungs contract to push air out" is always wrong.
Worked example. A resting student breathes 15 times a minute with a tidal volume of 500 cm3 and an anatomical dead space of 150 cm3. Find her minute volume and alveolar ventilation, and the alveolar ventilation if she keeps the same minute volume but breathes 30 times a minute.
Step 1: minute volume = 500 × 15 = 7,500 cm3 per minute.
Step 2: only 500 minus 150 = 350 cm3 of each breath reaches the alveoli, so alveolar ventilation = 350 × 15 = 5,250 cm3 per minute.
Step 3: at 30 breaths a minute each breath is 7,500 ÷ 30 = 250 cm3, of which only 100 cm3 reaches the alveoli: 100 × 30 = 3,000 cm3 per minute.
Answer: 7,500 and 5,250 cm3 per minute; rapid shallow breathing cuts alveolar ventilation to 3,000 cm3 per minute because more of every breath is wasted on the dead space.
B13.2 Gas transport and disorders
B13.2.1 Explain the transport of oxygen and carbon dioxide in blood (haemoglobin, Bohr effect)
Oxygen. Only about 2 to 3% of blood oxygen travels dissolved in plasma. The rest is carried in red blood cells bound to haemoglobin, a conjugated protein of four polypeptide chains (two alpha, two beta), each holding one haem group with a single iron ion, Fe2+. Each Fe2+ binds one O2 reversibly, so one molecule carries up to four:
Hb + 4O2 ⇌ Hb(O2)4
Loading (association) happens in the lungs where the partial pressure of oxygen is high; unloading (dissociation) happens in the tissues where it is low.
The oxygen dissociation curve plots percentage saturation of haemoglobin against partial pressure of oxygen. It is S-shaped (sigmoid) because of co-operative binding: once the first oxygen attaches, the shape of haemoglobin changes and the next three attach more easily. On the flat upper part haemoglobin is almost fully saturated (about 97 to 98%) at the alveolar partial pressure of 100 mmHg, and still about 90% if alveolar oxygen falls somewhat, as at altitude. On the steep middle part, in resting tissue at around 40 mmHg, saturation drops to about 75%, and a small further fall in tissue oxygen releases a large extra amount.
The Bohr effect is the control of unloading by carbon dioxide. Active tissue produces carbon dioxide, which forms carbonic acid and lowers the pH; hydrogen ions bind to haemoglobin and reduce its affinity for oxygen, so at any given partial pressure it is less saturated: the curve shifts to the right. A rise in temperature shifts it the same way. Haemoglobin therefore releases most oxygen where the metabolic rate is highest, while in the lungs, where carbon dioxide is low, loading is full. Fetal haemoglobin and myoglobin have curves to the left (higher affinity), so the fetus can draw oxygen from the mother's blood and muscle can store it.
Carbon dioxide is carried in three forms, and the proportions are a favourite recall question:
| Form | Where | Approximate share |
|---|---|---|
| Hydrogencarbonate (bicarbonate) ions, HCO3− | Mostly in the plasma, after forming inside red cells | About 70% |
| Carbaminohaemoglobin | In red cells, bound to amino groups of the globin chains, not to haem | About 20 to 25% |
| Dissolved CO2 | Plasma (CO2 is far more soluble than O2) | About 5 to 10% |
The hydrogencarbonate route in a tissue capillary:
- Carbon dioxide diffuses from the tissue into a red blood cell.
- Inside the red cell carbonic anhydrase combines it with water at great speed: CO2 + H2O ⇌ H2CO3. Without the enzyme this is far too slow.
- Carbonic acid dissociates: H2CO3 ⇌ H+ + HCO3−.
- Haemoglobin buffers the hydrogen ions (haemoglobinic acid); this same binding of H+ drives the Bohr effect and pushes oxygen off.
- Hydrogencarbonate ions diffuse out into the plasma, and chloride ions diffuse in to keep the red cell electrically neutral: the chloride shift.
In the lungs every step runs backwards: hydrogencarbonate re-enters the red cell and chloride leaves, carbonic anhydrase splits carbonic acid into water and carbon dioxide, and the carbon dioxide diffuses into the alveolus.
B13.2.2 Describe respiratory disorders and the effects of smoking
| Disorder | What goes wrong | Usual cause | Effect |
|---|---|---|---|
| Bronchitis | Inflamed bronchi with excess mucus | Infection (acute); smoke and polluted air (chronic) | Persistent cough with sputum |
| Emphysema | Alveolar walls break down into larger sacs; elastic tissue is lost | Smoking, mainly | Much smaller exchange surface, severe breathlessness; with chronic bronchitis forms COPD |
| Asthma | Bronchiole smooth muscle contracts, lining swells, mucus increases | Allergens (dust, pollen), exercise, cold air | Attacks of wheezing; relieved by inhaled bronchodilators |
| Pneumonia | Alveoli inflamed and filled with fluid, so diffusion distance rises and surface falls | Bacteria such as Streptococcus pneumoniae; also viruses, fungi | Fever, cough, chest pain, rapid shallow breathing |
| Tuberculosis (TB) | Bacteria form nodules (tubercles) that destroy lung tissue | Mycobacterium tuberculosis, spread in droplets | Chronic cough, blood in sputum, weight loss; prevented by BCG vaccine, treated with antibiotics |
| Lung cancer | Uncontrolled division of bronchial epithelium forms a tumour that blocks the airway and spreads | Carcinogens in tar; also asbestos | Persistent cough, blood in sputum, weight loss |
Tobacco smoke: MDCAT names three components.
- Tar: a sticky mixture of carcinogens. It destroys cilia, stimulates extra mucus (smoker's cough, chronic bronchitis), damages alveolar walls (emphysema) and over years causes cancer.
- Nicotine: the addictive drug. A stimulant that narrows blood vessels, raises heart rate and blood pressure and makes platelets stickier, raising the risk of thrombosis and heart attack.
- Carbon monoxide: a colourless, odourless gas from incomplete combustion. It binds haem more than 200 times more strongly than oxygen, forming stable carboxyhaemoglobin, so the oxygen-carrying capacity of the blood falls; a smoker's fetus is starved of oxygen and born underweight.
MDCAT trap: a right shift is about letting go, not carrying more. When a question says carbon dioxide, acidity or temperature has risen and the dissociation curve has moved right, many students pick "haemoglobin carries more oxygen". That is backwards. A right shift means that at any given partial pressure haemoglobin is less saturated: it holds oxygen less tightly and releases a larger share to the tissues, while loading in the lungs barely changes because the lungs sit on the flat top of the curve. So the Bohr effect raises oxygen delivery, not oxygen carriage. What actually cuts the oxygen the blood can carry is something that blocks haem, such as carbon monoxide, or too little haemoglobin, as in anaemia.
Worked example. In the lungs (100 mmHg) haemoglobin is 98% saturated. In resting muscle (40 mmHg) the normal curve gives 75%. In hard exercise the muscle partial pressure falls to 20 mmHg, and the extra carbon dioxide, acid and heat shift the curve right so that saturation at 20 mmHg is 20% instead of the 35% the unshifted curve would give. What percentage of its oxygen does haemoglobin unload in the resting and the exercising muscle, and how much of the extra unloading is due to the Bohr effect?
Step 1: unloading = saturation on arrival minus saturation on leaving. Resting muscle: 98 minus 75 = 23%.
Step 2: exercising muscle with the shifted curve: 98 minus 20 = 78%.
Step 3: the fall in partial pressure alone (unshifted curve at 20 mmHg) would release 98 minus 35 = 63%; the right shift adds 35 minus 20 = 15%.
Answer: 23% at rest, 78% in exercise; of the extra 55%, 40% comes from the lower partial pressure and 15% from the Bohr shift. Loading in the lungs stayed at 98%.
Practice MCQs
- Which part of the human respiratory tract has smooth muscle in its wall but no cartilage?
A. Trachea
B. Primary bronchus
C. Bronchiole
D. Larynx - Which statement correctly describes quiet inspiration in a resting person?
A. The diaphragm relaxes and domes upwards, increasing the volume of the thorax.
B. The internal intercostal muscles contract and pull the ribs downwards.
C. The pressure in the alveoli rises above atmospheric pressure, pulling air in.
D. The volume of the thorax increases, so the pressure in the alveoli falls below atmospheric pressure. - A man has a vital capacity of 4.6 dm3, a tidal volume of 0.5 dm3, an expiratory reserve volume of 1.1 dm3 and a residual volume of 1.2 dm3. His inspiratory reserve volume is
A. 3.0 dm3
B. 3.4 dm3
C. 4.1 dm3
D. 5.8 dm3 - A patient breathes 12 times a minute with a tidal volume of 500 cm3 and has an anatomical dead space of 150 cm3. The volume of fresh air reaching her alveoli each minute is
A. 6,000 cm3
B. 4,200 cm3
C. 1,800 cm3
D. 350 cm3 - The lungs contain no skeletal muscle, yet they enlarge whenever the thorax enlarges. This is because
A. the thin film of pleural fluid holds the surface of each lung to the chest wall.
B. the lungs are joined to the ribs by short tendons.
C. the air pressure inside the alveoli pushes the lungs outwards against the ribs.
D. the diaphragm is attached directly to the base of each lung. - After a student runs upstairs her breathing becomes faster and deeper. The main stimulus for this change is
A. a fall in the oxygen concentration of her plasma, detected by the cerebellum.
B. stretching of the alveolar walls, detected by stretch receptors in the lungs.
C. a rise in blood pressure, detected by baroreceptors in the aorta.
D. a rise in the carbon dioxide concentration of her blood, detected by chemoreceptors in the medulla. - Which combination of conditions in a capillary shifts the oxygen dissociation curve of haemoglobin to the right?
A. Low carbon dioxide and high pH
B. Low temperature and high partial pressure of oxygen
C. High carbon dioxide and low pH
D. High pH and high temperature - Most of the carbon dioxide produced by the tissues is carried to the lungs
A. dissolved in the plasma.
B. as hydrogencarbonate ions in the plasma.
C. as carbaminohaemoglobin in red blood cells.
D. as carbonic acid inside red blood cells. - In a capillary in active muscle, hydrogencarbonate ions formed inside the red blood cells diffuse out into the plasma. Which movement across the red cell membrane accompanies this?
A. Chloride ions move into the red cell.
B. Chloride ions move out of the red cell.
C. Hydrogen ions move out into the plasma.
D. Sodium ions move into the red cell. - A heavy smoker becomes severely breathless. His doctor finds that the walls between many of his alveoli have broken down and his lungs have lost their elastic recoil. The disorder is
A. pneumonia.
B. asthma.
C. tuberculosis.
D. emphysema.
1 C. Bronchioles have smooth muscle but no cartilage; the trachea, bronchi and larynx all contain cartilage.
2 D. The diaphragm flattens and the external intercostals lift the ribs, volume rises, alveolar pressure falls below atmospheric, and air flows in; the other options each reverse one step.
3 A. Vital capacity = TV + IRV + ERV, so IRV = 4.6 minus 0.5 minus 1.1 = 3.0 dm3.
4 B. Only 500 minus 150 = 350 cm3 of each breath reaches the alveoli; 350 × 12 = 4,200 cm3 per minute. Option A forgets the dead space.
5 A. The surface tension of the pleural fluid holds the visceral and parietal pleurae together, so the lungs follow the chest wall.
6 D. Carbon dioxide, acting through hydrogen ions, is the main stimulus to the respiratory centre in the medulla; oxygen matters only when it falls severely.
7 C. High carbon dioxide, low pH and high temperature all lower the affinity of haemoglobin for oxygen and move the curve right (the Bohr effect).
8 B. About 70% of carbon dioxide travels as hydrogencarbonate ions in the plasma, formed inside red cells by carbonic anhydrase.
9 A. When negatively charged HCO3− leaves the red cell, Cl− enters to keep it electrically neutral: the chloride shift. Hydrogen ions stay inside, buffered by haemoglobin.
10 D. Breakdown of alveolar walls and loss of elastic recoil define emphysema; pneumonia fills alveoli with fluid, asthma narrows bronchioles, tuberculosis forms tubercles.
Before the test: 12 facts to recite
- Route of air: nasal cavity → pharynx → larynx → trachea → bronchi → bronchioles → alveoli; gas exchange only in the alveoli, by diffusion alone.
- Trachea and bronchi have cartilage and a ciliated, goblet-cell lining; bronchioles have smooth muscle and no cartilage; the alveolar wall is one cell thick.
- Alveoli are efficient because of thin walls, a moist lining with surfactant, a huge surface area and a dense capillary network.
- Inspiration is active: diaphragm contracts and flattens, external intercostals lift the ribs, volume up, pressure down, air in.
- Quiet expiration is passive (relaxation plus elastic recoil); forced expiration uses the internal intercostals and the abdominal muscles.
- Breathing rhythm comes from the medulla oblongata; a rise in blood carbon dioxide is the main stimulus to breathe faster.
- Tidal volume about 500 cm3; vital capacity = TV + IRV + ERV; total lung capacity = VC + RV; minute volume = TV × rate.
- Haemoglobin has four haem groups, each with one Fe2+, so one molecule carries four O2; about 97% of blood oxygen is carried as oxyhaemoglobin.
- The oxygen dissociation curve is sigmoid; haemoglobin loads on the flat top (lungs, about 98%) and unloads on the steep middle (resting tissue, about 75%).
- Bohr effect: more carbon dioxide, lower pH or higher temperature shifts the curve right, so haemoglobin releases more oxygen to active tissue.
- Carbon dioxide travels about 70% as hydrogencarbonate ions in the plasma (made in red cells by carbonic anhydrase; chloride shift balances the charge), about 20 to 25% as carbaminohaemoglobin, about 5 to 10% dissolved.
- Smoke: tar causes cancer, destroys cilia and leads to bronchitis and emphysema; nicotine is addictive and raises heart rate and blood pressure; carbon monoxide forms carboxyhaemoglobin and cuts oxygen carriage.
