
MDCAT · Biology (PMDC curriculum) · Unit 9: Support and movement
MDCAT Biology Unit 9: Support and movement, study guide with practice MCQs
Need more than one subject? All-notes pass: unlimited downloads of every note for a year: unlimited downloads of every note on the site, PKR 999 a year. All packs and courses.
Opens inside this page. Prefer your own PDF app? Open the PDF.
Check yourself
5 quick questions on MDCAT Biology
Tap an answer to see if you are right, and why. Free, no sign-up.
Start the free testWas this note useful?
Full text of MDCAT Biology Unit 9: Support and movement, study guide with practice MCQs
What MDCAT asks
This unit covers the human skeleton (bone, cartilage, the bone count and the vertebral column), the three classes of joint with two common skeletal disorders, and then the structure of skeletal muscle, the sarcomere, the sliding filament model and the comparison of skeletal, smooth and cardiac muscle. Its two subtopics carry equal weight and together are worth roughly two to three of the 81 Biology questions. The questions are mostly factual: which band changes during contraction, which bone cell does what, which joint is which, and short comparisons, so precise recall of a small set of facts pays well here.
B9.1 Skeleton and joints
B9.1.1 Describe the human skeleton, bone and cartilage
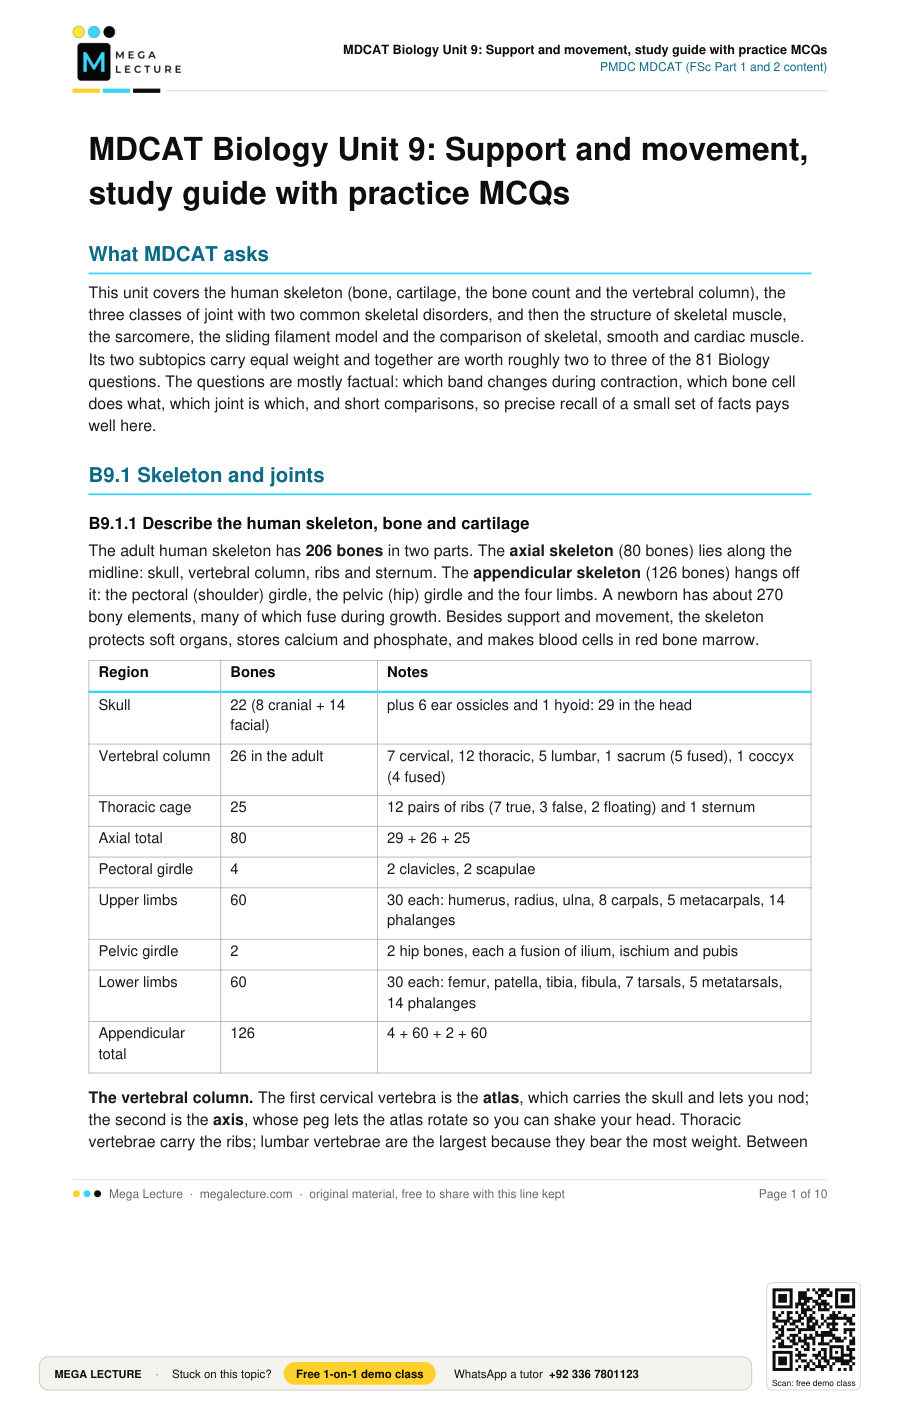
The adult human skeleton has 206 bones in two parts. The axial skeleton (80 bones) lies along the midline: skull, vertebral column, ribs and sternum. The appendicular skeleton (126 bones) hangs off it: the pectoral (shoulder) girdle, the pelvic (hip) girdle and the four limbs. A newborn has about 270 bony elements, many of which fuse during growth. Besides support and movement, the skeleton protects soft organs, stores calcium and phosphate, and makes blood cells in red bone marrow.
| Region | Bones | Notes |
|---|---|---|
| Skull | 22 (8 cranial + 14 facial) | plus 6 ear ossicles and 1 hyoid: 29 in the head |
| Vertebral column | 26 in the adult | 7 cervical, 12 thoracic, 5 lumbar, 1 sacrum (5 fused), 1 coccyx (4 fused) |
| Thoracic cage | 25 | 12 pairs of ribs (7 true, 3 false, 2 floating) and 1 sternum |
| Axial total | 80 | 29 + 26 + 25 |
| Pectoral girdle | 4 | 2 clavicles, 2 scapulae |
| Upper limbs | 60 | 30 each: humerus, radius, ulna, 8 carpals, 5 metacarpals, 14 phalanges |
| Pelvic girdle | 2 | 2 hip bones, each a fusion of ilium, ischium and pubis |
| Lower limbs | 60 | 30 each: femur, patella, tibia, fibula, 7 tarsals, 5 metatarsals, 14 phalanges |
| Appendicular total | 126 | 4 + 60 + 2 + 60 |
The vertebral column. The first cervical vertebra is the atlas, which carries the skull and lets you nod; the second is the axis, whose peg lets the atlas rotate so you can shake your head. Thoracic vertebrae carry the ribs; lumbar vertebrae are the largest because they bear the most weight. Between vertebrae lie intervertebral discs of fibrocartilage, which absorb shock and allow slight bending.
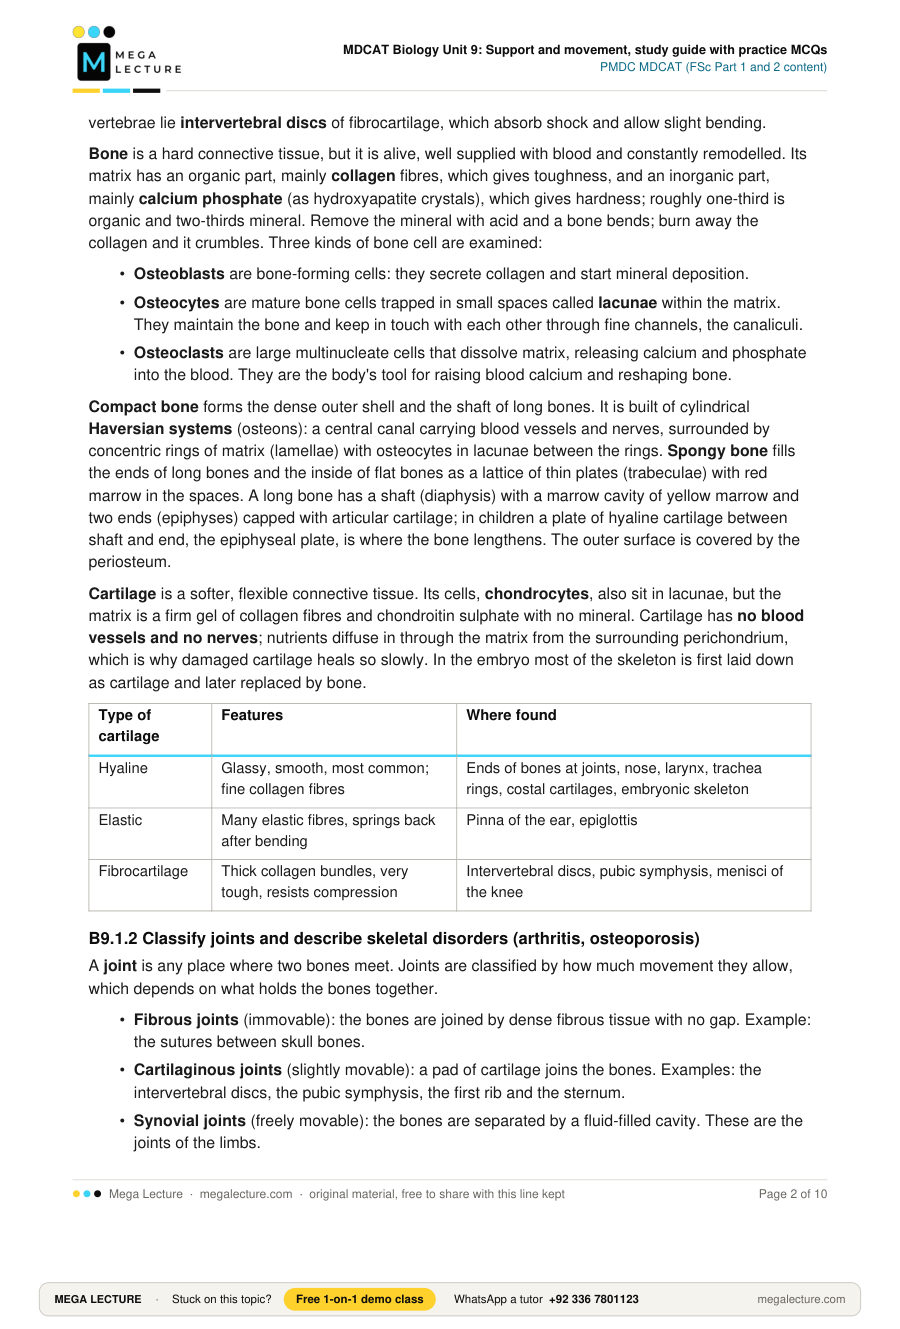
Bone is a hard connective tissue, but it is alive, well supplied with blood and constantly remodelled. Its matrix has an organic part, mainly collagen fibres, which gives toughness, and an inorganic part, mainly calcium phosphate (as hydroxyapatite crystals), which gives hardness; roughly one-third is organic and two-thirds mineral. Remove the mineral with acid and a bone bends; burn away the collagen and it crumbles. Three kinds of bone cell are examined:
- Osteoblasts are bone-forming cells: they secrete collagen and start mineral deposition.
- Osteocytes are mature bone cells trapped in small spaces called lacunae within the matrix. They maintain the bone and keep in touch with each other through fine channels, the canaliculi.
- Osteoclasts are large multinucleate cells that dissolve matrix, releasing calcium and phosphate into the blood. They are the body's tool for raising blood calcium and reshaping bone.
Compact bone forms the dense outer shell and the shaft of long bones. It is built of cylindrical Haversian systems (osteons): a central canal carrying blood vessels and nerves, surrounded by concentric rings of matrix (lamellae) with osteocytes in lacunae between the rings. Spongy bone fills the ends of long bones and the inside of flat bones as a lattice of thin plates (trabeculae) with red marrow in the spaces. A long bone has a shaft (diaphysis) with a marrow cavity of yellow marrow and two ends (epiphyses) capped with articular cartilage; in children a plate of hyaline cartilage between shaft and end, the epiphyseal plate, is where the bone lengthens. The outer surface is covered by the periosteum.
Cartilage is a softer, flexible connective tissue. Its cells, chondrocytes, also sit in lacunae, but the matrix is a firm gel of collagen fibres and chondroitin sulphate with no mineral. Cartilage has no blood vessels and no nerves; nutrients diffuse in through the matrix from the surrounding perichondrium, which is why damaged cartilage heals so slowly. In the embryo most of the skeleton is first laid down as cartilage and later replaced by bone.
| Type of cartilage | Features | Where found |
|---|---|---|
| Hyaline | Glassy, smooth, most common; fine collagen fibres | Ends of bones at joints, nose, larynx, trachea rings, costal cartilages, embryonic skeleton |
| Elastic | Many elastic fibres, springs back after bending | Pinna of the ear, epiglottis |
| Fibrocartilage | Thick collagen bundles, very tough, resists compression | Intervertebral discs, pubic symphysis, menisci of the knee |
B9.1.2 Classify joints and describe skeletal disorders (arthritis, osteoporosis)
A joint is any place where two bones meet. Joints are classified by how much movement they allow, which depends on what holds the bones together.
- Fibrous joints (immovable): the bones are joined by dense fibrous tissue with no gap. Example: the sutures between skull bones.
- Cartilaginous joints (slightly movable): a pad of cartilage joins the bones. Examples: the intervertebral discs, the pubic symphysis, the first rib and the sternum.
- Synovial joints (freely movable): the bones are separated by a fluid-filled cavity. These are the joints of the limbs.
A synovial joint has a fixed set of parts. The bone ends are covered with smooth articular (hyaline) cartilage that reduces friction. A fibrous joint capsule surrounds the joint and is lined by the synovial membrane, which secretes synovial fluid into the joint cavity; the fluid lubricates the joint, feeds the cartilage and absorbs shock. Ligaments, bands of tough fibrous tissue running from bone to bone, limit the movement so the joint does not dislocate.
| Synovial joint | Movement | Examples |
|---|---|---|
| Hinge | One plane only (flexion and extension), like a door | Elbow, knee, finger joints |
| Ball and socket | All planes including rotation; the most freely movable | Shoulder, hip |
| Pivot | Rotation around a long axis | Atlas on axis (shaking the head), radius on ulna (turning the palm) |
| Gliding (plane) | Short sliding movements | Between carpals, between tarsals |
| Saddle | Back and forth and side to side, no rotation | Base of the thumb |
| Condyloid | Two planes, no rotation | Wrist, knuckles |
Arthritis means inflammation of a joint. Two forms are examined and the difference between them is a favourite question.
- Osteoarthritis is a degenerative wear-and-tear disease. The articular cartilage wears away with age and heavy use, bone rubs on bone and bony spurs form at the joint edges. It affects the large weight-bearing joints (knees, hips, spine) and the fingers, mostly in older people. The joint is painful and stiff after use, with little swelling and no general illness.
- Rheumatoid arthritis is an autoimmune disease. The immune system attacks the synovial membrane, which becomes inflamed and thickened, and the inflammation then erodes cartilage and bone so the joint can become deformed. It usually starts in the small joints of the hands and feet, symmetrically on both sides, with marked morning stiffness and swelling, can begin at any age, and often brings tiredness and fever because the whole immune system is involved.
Osteoporosis is a disease of bone, not of joints. Normally osteoclasts remove old bone and osteoblasts replace it; in osteoporosis removal outpaces replacement, bone mass falls, spongy bone becomes porous and thin, and bones break after trivial falls, typically the hip, the wrist and the vertebrae (which crumble, giving loss of height and a stooped back). It is most common in women after the menopause, because oestrogen normally restrains osteoclasts and its level drops sharply. Other risks are old age, low calcium or vitamin D intake, lack of weight-bearing exercise, smoking and long steroid treatment; prevention is a calcium-rich diet, vitamin D and regular exercise while bone is still being built. Do not confuse it with rickets, in which a child's bones are soft and bend because vitamin D deficiency leaves them poorly mineralised. Two back problems from the FSc books deserve a line: in a slipped disc the soft centre of an intervertebral disc bulges through its fibrous ring and presses on a spinal nerve, and when that nerve is the sciatic nerve the pain down the back of the leg is called sciatica.
MDCAT trap: blasts build, clasts cut away. Osteoblasts and osteoclasts are swapped in more wrong answers than any other pair in this unit. Fix the words: a blast is a builder cell everywhere in biology (osteoblast, chondroblast, fibroblast), so osteoblasts lay down new matrix; a clast breaks (as in "iconoclast"), so osteoclasts dissolve matrix. The two work together: remodelling, fracture repair and the control of blood calcium all need both. The trap questions run like this: "Which cell raises blood calcium?" (osteoclast, because dissolving matrix releases Ca2+); "Which cell is relatively overactive in osteoporosis?" (osteoclast); "Which cell sits in a lacuna?" (osteocyte, the mature cell, not either of the others). A second trap: cartilage cells are chondrocytes, not osteocytes, and cartilage has no blood supply whereas bone has a rich one, which is why bone heals in weeks and cartilage barely heals at all.
Worked example. How many separate bones make up the adult vertebral column, and how many vertebrae were there before fusion?
- Count the movable vertebrae: 7 cervical + 12 thoracic + 5 lumbar = 24.
- In the adult the sacrum is one bone (5 fused) and the coccyx one bone (4 fused): 24 + 1 + 1 = 26.
- Before fusion: 24 + 5 + 4 = 33 vertebrae.
- Check against the axial count: 29 (head) + 26 (column) + 25 (ribs and sternum) = 80.
Answer: 26 bones in the adult column, from 33 vertebrae in the child. A question offering 33 as the adult number is testing exactly this.
B9.2 Muscles and contraction
B9.2.1 Describe the structure of skeletal muscle and the sarcomere
A skeletal muscle is a bundle of bundles. The whole muscle is wrapped in connective tissue and attached to bone by tendons. Inside are bundles of muscle fibres. Each fibre is one very long cell, up to several centimetres long and 10 to 100 μm wide, formed in the embryo by fusion of many cells, so it has many nuclei pushed to the edge. Its membrane is the sarcolemma and its cytoplasm the sarcoplasm. Through the sarcoplasm run hundreds of parallel threads, the myofibrils, each wrapped in a membrane network, the sarcoplasmic reticulum, which stores calcium ions. Tube-like infoldings of the sarcolemma, the T tubules, carry the electrical signal deep into the fibre, and many mitochondria lie between the myofibrils to supply ATP.
Each myofibril is a chain of identical repeating units, the sarcomeres, the contractile units of muscle. A sarcomere runs from one Z line to the next and is about 2 to 2.5 μm long when relaxed. It holds two kinds of parallel protein filament:
- Thin filaments are made of actin (two twisted strands of globular actin) with a long rod of tropomyosin lying in the groove and a troponin complex at intervals. They are anchored to the Z lines and point towards the middle of the sarcomere.
- Thick filaments are made of myosin, a protein with a long tail and a globular head. Hundreds of myosin molecules bundle into one thick filament with the heads sticking out on all sides; the heads are ATPases with binding sites for actin. Thick filaments lie in the middle of the sarcomere, held at their centre by the M line.
Because the filaments overlap in a regular pattern, the myofibril shows alternating light and dark stripes, which is why skeletal muscle is called striated. The names of the stripes are the most tested fact in this unit.
| Region | What it contains | Appearance | During contraction |
|---|---|---|---|
| A band | The whole length of the thick (myosin) filaments, including the overlap with actin | Dark | Stays the same length |
| I band | Thin (actin) filaments only, either side of a Z line; half belongs to each neighbouring sarcomere | Light | Shortens |
| H zone | Middle of the A band, myosin only, no actin | Slightly paler than the rest of the A band | Shortens, may disappear |
| Z line | Protein disc anchoring the thin filaments; the sarcomere boundary | Dark line in the middle of the I band | Z lines move closer together |
| M line | Proteins holding the thick filaments in the centre of the H zone | Fine central line | Position unchanged |
Two whole-muscle terms are examined too. A tendon is a cord of dense collagen joining muscle to bone; a ligament joins bone to bone. The attachment of a muscle to the bone that stays still is its origin; the attachment to the bone that moves is its insertion. The biceps has its origin on the scapula and its insertion on the radius, so when it contracts the forearm moves and the shoulder does not.
B9.2.2 Explain the sliding filament model and compare skeletal, smooth and cardiac muscle
The sliding filament model explains how a sarcomere shortens. The filaments never change length. Instead the myosin heads pull the thin filaments inward past the thick filaments towards the M line, so the overlap increases and the Z lines are dragged closer together. Every sarcomere in the myofibril shortens by a little at the same time, so the whole fibre shortens.
Starting the contraction. A motor neurone ends on the fibre at the neuromuscular junction, where it releases acetylcholine. This depolarises the sarcolemma, and the action potential spreads along the fibre and down the T tubules. The sarcoplasmic reticulum responds by releasing Ca2+ into the sarcoplasm. Calcium binds to troponin, which changes shape and pulls tropomyosin away from the myosin-binding sites on actin, exposing them.
The cross-bridge cycle, four steps that repeat:
- A myosin head, already carrying ADP and inorganic phosphate (Pi) from an earlier ATP hydrolysis, binds to an exposed site on actin, forming a cross-bridge.
- The head releases Pi and ADP and tilts: the power stroke, which pulls the thin filament a short distance towards the centre of the sarcomere.
- A fresh ATP binds to the head, and this binding makes the head let go of actin.
- The head hydrolyses the ATP to ADP + Pi, which re-cocks it, ready to attach further along the actin.
Each cycle uses one ATP per head, and the many heads work out of step, like a team pulling a rope hand over hand, so the thin filament is never released entirely. Contraction continues as long as Ca2+ and ATP are present. Relaxation follows when the nerve stops firing: Ca2+ is pumped back into the sarcoplasmic reticulum by active transport (also using ATP), troponin returns to its original shape, tropomyosin covers the binding sites again, and the muscle is stretched back by its antagonist or the load.
ATP therefore has two jobs: its hydrolysis powers the cocking of the head, and its binding is needed for detachment. The second explains rigor mortis: after death no ATP is made, so attached heads cannot let go, Ca2+ leaks from the sarcoplasmic reticulum so more heads attach, and the muscles lock until the proteins themselves break down a day or two later.
Energy and fatigue. A fibre holds only a few seconds' worth of ATP. It is topped up first from creatine phosphate, which hands its phosphate to ADP almost instantly and lasts about 10 to 15 seconds, then from glycolysis of stored glycogen, which is fast but produces lactic acid, and in longer activity from aerobic respiration. The lactic acid built up in hard exercise is cleared afterwards using extra oxygen, the oxygen debt. Muscle fatigue is the fall in force after prolonged activity, usually blamed on lactic acid accumulation and depletion of glycogen and ATP. A cramp is a sudden painful involuntary contraction that does not relax. Tetany is twitching and spasm caused by low blood calcium, which makes nerves fire too easily; do not confuse it with tetanus, the smooth sustained contraction produced when impulses arrive so fast that twitches fuse.
Antagonistic pairs. A muscle can only pull, never push, so each movement needs a second muscle to reverse it. At the elbow the biceps is the flexor (bends the joint) and the triceps the extensor (straightens it); when one contracts the other relaxes and is stretched. Contraction that shortens the muscle and moves a load is isotonic; contraction that produces tension without shortening, as when pushing against a wall, is isometric.
The three types of muscle are compared almost every year in some form, so learn the table.
| Feature | Skeletal muscle | Cardiac muscle | Smooth muscle |
|---|---|---|---|
| Where | Attached to bones; also tongue, diaphragm | Heart wall only | Walls of gut, blood vessels, bladder, uterus, airways, iris |
| Striations | Yes (sarcomeres) | Yes (sarcomeres) | No: actin and myosin present but not in sarcomeres |
| Cell shape | Very long cylindrical fibres, unbranched | Shorter fibres that branch and join end to end | Small spindle-shaped cells |
| Nuclei | Many, at the edge | Usually one, central | One, central |
| Special feature | Neuromuscular junctions, well-developed T tubules | Intercalated discs with gap junctions, so impulses pass cell to cell | No T tubules; cells often linked by gap junctions |
| Control | Voluntary (somatic nerves) | Involuntary; beats on its own (myogenic), rate set by autonomic nerves and hormones | Involuntary (autonomic nerves, hormones, stretch) |
| Speed and fatigue | Fast, powerful, fatigues | Rhythmic, never fatigues; long refractory period, cannot go into tetanus | Slow, stays contracted for long periods without fatigue |
MDCAT trap: the filaments do not shorten, and the A band never changes. Students write that "actin and myosin contract" or that "the A band shortens". Neither is true. The filaments keep exactly the same length; they slide, which is the whole point of the model's name. The A band is the length of the myosin filament, so it cannot change. What changes is the overlap: the I band (actin not overlapped by myosin) and the H zone (myosin not overlapped by actin) both get shorter, and the Z lines move closer. If a sarcomere shortens by 0.3 μm, the H zone shortens by 0.3 μm and the total I band by 0.3 μm, while the A band is unchanged. A second trap: calcium binds troponin, not tropomyosin and not myosin; tropomyosin is the rod that moves aside. A third: ATP is needed for the myosin head to detach; with no ATP the head stays stuck, which is why a dead muscle is stiff, not limp.
Worked example. A relaxed sarcomere is 2.4 μm long with an A band of 1.6 μm and an H zone of 0.6 μm. (a) How long is one thin (actin) filament? (b) The sarcomere contracts to 2.0 μm. Give the new A band, total I band and H zone lengths.
- (a) Each thin filament runs from a Z line to the edge of the H zone, so the two thin filaments together cover everything except the H zone: 2.4 − 0.6 = 1.8 μm, and one thin filament is 1.8 ÷ 2 = 0.9 μm.
- (b) The A band equals the myosin length and does not change: 1.6 μm.
- Total I band = sarcomere − A band = 2.0 − 1.6 = 0.4 μm (it was 2.4 − 1.6 = 0.8 μm).
- The sarcomere shortened by 2.4 − 2.0 = 0.4 μm, so the H zone shortened by the same amount: 0.6 − 0.4 = 0.2 μm.
- Check: (2.0 − 0.2) ÷ 2 = 0.9 μm, the thin filament length is unchanged.
Answer: (a) 0.9 μm; (b) A band 1.6 μm, I band 0.4 μm, H zone 0.2 μm.
Practice MCQs
- Which of the following bones belongs to the axial skeleton?
A. Scapula
B. Sternum
C. Humerus
D. Hip bone - A patient's blood calcium level has fallen below normal. Which bone cell activity would the body increase to correct it?
A. Osteoblasts depositing new matrix
B. Osteocytes sensing stress in lacunae
C. Osteoclasts dissolving matrix
D. Chondrocytes dividing in the epiphyseal plate - A tissue has cells lying in lacunae within a firm, flexible matrix that contains no blood vessels. It is most likely
A. Hyaline cartilage
B. Compact bone
C. Spongy bone
D. Tendon - Turning the head from side to side to signal "no" is a movement at the joint between the atlas and the axis. This joint is a
A. Hinge joint
B. Ball and socket joint
C. Gliding joint
D. Pivot joint - A 68-year-old woman has lost height over several years and has fractured a vertebra after a minor fall. Her joints are not swollen or hot, and an X-ray shows bones of low density. The most likely diagnosis is
A. Rheumatoid arthritis
B. Osteoarthritis
C. Osteoporosis
D. Rickets - The H zone of a sarcomere contains
A. Myosin filaments only
B. Actin filaments only
C. Overlapping actin and myosin
D. The Z line - A few hours after death the muscles of the body become stiff. The direct cause is that
A. Calcium can no longer be released from the sarcoplasmic reticulum
B. Without ATP the myosin heads cannot detach from actin
C. Tropomyosin permanently covers the binding sites on actin
D. Lactic acid denatures the myosin heads - During contraction of a sarcomere, which of these remains the same length?
A. The I band
B. The H zone
C. The distance between Z lines
D. The A band - A relaxed sarcomere is 2.0 μm long and its A band is 1.6 μm. After contraction the sarcomere measures 1.8 μm. The total length of the I band in the contracted sarcomere is
A. 0.2 μm
B. 0.4 μm
C. 1.6 μm
D. 1.8 μm - A muscle sample shows striated fibres that branch and join one another through specialised junctions, each cell with a single central nucleus. The sample is from the
A. Wall of the intestine
B. Biceps brachii
C. Wall of an artery
D. Heart
Answer key
- B. The sternum, with the skull, vertebral column and ribs, makes up the axial skeleton; the scapula, humerus and hip bone are appendicular.
- C. Osteoclasts dissolve bone matrix and release calcium and phosphate into the blood; osteoblasts would do the opposite by locking calcium into new bone.
- A. Cells in lacunae plus a flexible, avascular matrix describes cartilage; bone also has lacunae but its matrix is mineralised and well supplied with blood, and tendon has no lacunae.
- D. The atlas rotates around the peg of the axis, rotation about a long axis, which is the definition of a pivot joint. Nodding "yes" happens between the skull and the atlas.
- C. Low bone density, vertebral collapse with loss of height, fracture after a trivial fall and no joint inflammation in a postmenopausal woman is osteoporosis. Rickets is a childhood disease of soft, poorly mineralised bone.
- A. The H zone is the central part of the A band that the thin filaments do not reach, so only myosin is present.
- B. ATP binding is what makes a myosin head let go of actin; after death ATP runs out, the attached heads stay locked and the muscle is rigid (rigor mortis).
- D. The A band is the full length of the thick filaments, which do not change length; the I band and H zone shorten and the Z lines move closer together.
- A. Total I band = sarcomere length − A band = 1.8 − 1.6 = 0.2 μm (it was 0.4 μm when relaxed); the A band stays 1.6 μm.
- D. Striated, branched fibres joined by intercalated discs with one central nucleus is cardiac muscle. Gut and artery walls are smooth muscle (no striations); the biceps is skeletal (unbranched, many nuclei).
Before the test: 12 facts to recite
- 206 bones in the adult: axial 80 (skull, vertebral column, ribs, sternum) and appendicular 126 (girdles and limbs); 30 bones in each limb.
- Vertebrae: 7 cervical, 12 thoracic, 5 lumbar, sacrum (5 fused), coccyx (4 fused); 33 before fusion, 26 bones in the adult. Ribs: 12 pairs, 7 true, 3 false, 2 floating.
- Bone matrix is collagen (toughness) plus calcium phosphate (hardness); compact bone is built of Haversian systems, spongy bone of trabeculae with red marrow.
- Osteoblasts build, osteocytes maintain (in lacunae), osteoclasts dissolve and release calcium.
- Cartilage: chondrocytes in lacunae, no blood vessels, heals slowly. Hyaline at joint surfaces, nose and trachea; elastic in the pinna and epiglottis; fibrocartilage in intervertebral discs and the pubic symphysis.
- Joints: fibrous, immovable (skull sutures); cartilaginous, slightly movable (between vertebrae); synovial, freely movable (articular cartilage, capsule, synovial membrane and fluid, ligaments).
- Synovial types: hinge (elbow, knee), ball and socket (shoulder, hip), pivot (atlas and axis), gliding (carpals), saddle (thumb), condyloid (wrist).
- Osteoarthritis: cartilage wears away with age, large joints. Rheumatoid arthritis: autoimmune attack on the synovial membrane, small joints, symmetrical, any age. Osteoporosis: porous low-mass bone, common after the menopause as oestrogen falls.
- Muscle fibre (many nuclei, sarcolemma, sarcoplasmic reticulum storing Ca2+, T tubules) → myofibrils → sarcomeres from Z line to Z line; thin filaments are actin with tropomyosin and troponin, thick filaments are myosin.
- A band = myosin length, dark, unchanged; I band = actin only, light, shortens; H zone = myosin only, shortens; Z lines move closer. The filaments slide, they do not shorten.
- Acetylcholine → action potential → Ca2+ from the sarcoplasmic reticulum → binds troponin → tropomyosin moves → myosin heads bind actin, power stroke, ATP binds to detach, ATP hydrolysed to re-cock. No ATP, no detachment: rigor mortis.
- Skeletal: striated, voluntary, many nuclei, unbranched. Cardiac: striated, involuntary, branched, intercalated discs, one central nucleus. Smooth: unstriated, involuntary, spindle cells, one nucleus, gut and vessels. Tendon joins muscle to bone, ligament joins bone to bone; origin fixed, insertion moves.
