
MDCAT · Biology (PMDC curriculum) · Unit 8: Reproduction
MDCAT Biology Unit 8: Reproduction, study guide with practice MCQs
Need more than one subject? All-notes pass: unlimited downloads of every note for a year: unlimited downloads of every note on the site, PKR 999 a year. All packs and courses.

Opens inside this page. Prefer your own PDF app? Open the PDF.
Check yourself
5 quick questions on MDCAT Biology
Tap an answer to see if you are right, and why. Free, no sign-up.
Start the free testWas this note useful?
Full text of MDCAT Biology Unit 8: Reproduction, study guide with practice MCQs
What MDCAT asks
This unit covers the human male and female reproductive systems, the making of sperm and ova, the hormonal control of the menstrual cycle, fertilisation, implantation, the placenta, the stages of development and the common sexually transmitted diseases. Its two subtopics together carry roughly 2 to 3 of the 81 Biology questions, split about evenly between them. The questions are mostly recall of hormones, cells and chromosome numbers, with the occasional one-step calculation on the cycle or on gamete numbers.
B8.1 Human reproductive systems
B8.1.1 The male and female reproductive systems and their functions
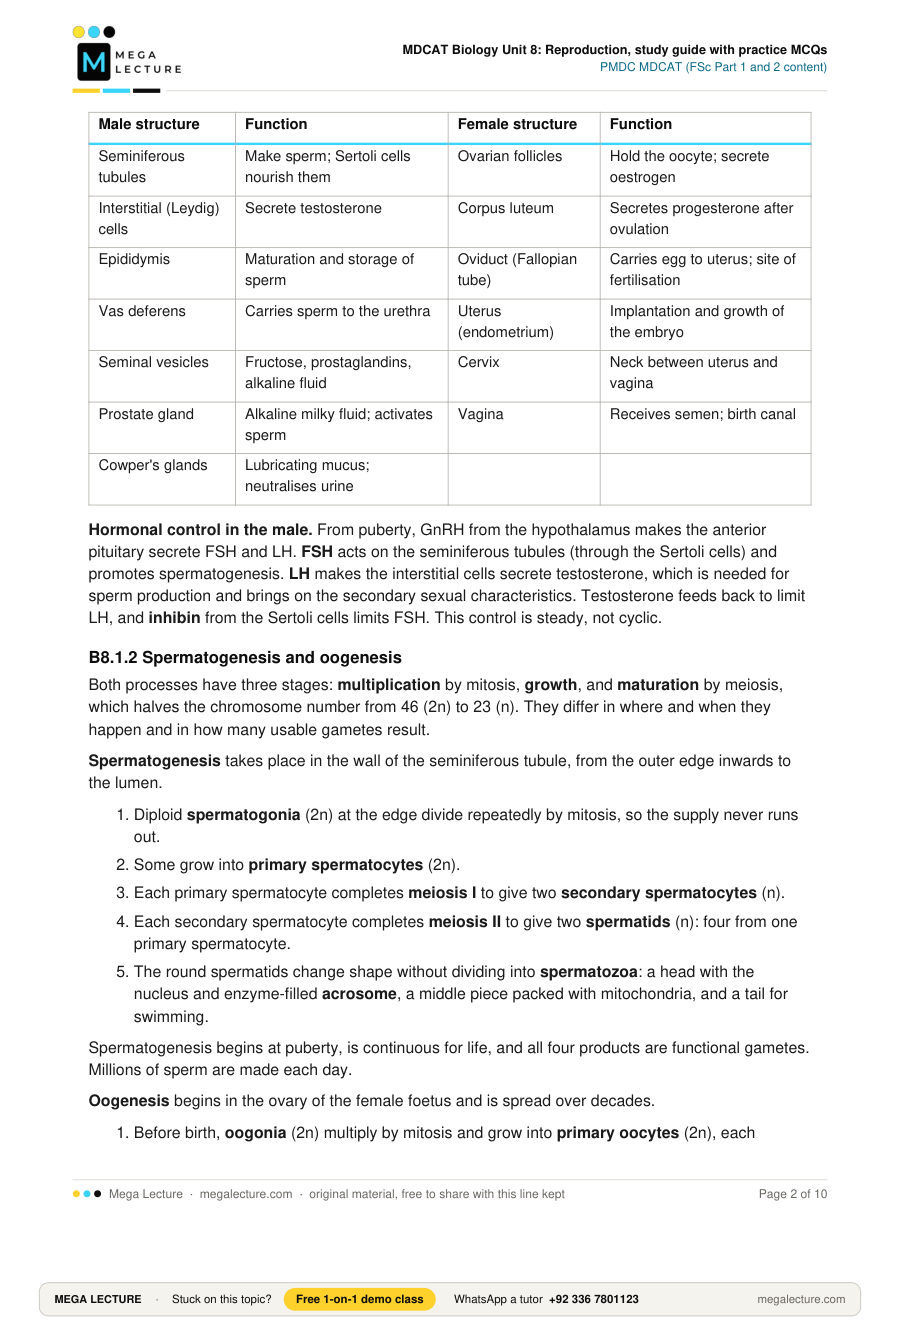
Male system. The two testes hang in the scrotum, about 2 to 3 °C cooler than the body core, because sperm do not form properly at full body temperature. Each testis is packed with coiled seminiferous tubules, whose walls hold the germinal epithelium where sperm are made and the Sertoli cells that nourish them. Between the tubules lie the interstitial cells (Leydig cells), which secrete testosterone. One organ, two jobs: gametes from the tubules, hormone from the cells between them.
Sperm leave the tubules immature and non-motile. In the epididymis, a coiled tube on the back of each testis, they mature, gain motility and are stored. At ejaculation they pass along the vas deferens, which loops over the bladder and, with the duct of the seminal vesicle, forms the ejaculatory duct opening into the urethra. Three sets of glands add fluid to make semen:
- Seminal vesicles (paired): most of the fluid; alkaline, with fructose as the energy source for sperm and prostaglandins that stimulate contractions of the female tract.
- Prostate gland (single, below the bladder): thin, milky, alkaline fluid that neutralises the acidity of the vagina and activates the sperm.
- Cowper's glands (bulbourethral, paired): clear mucus released before ejaculation that lubricates the urethra and clears acidic urine from it.
Female system. The two ovaries hold thousands of follicles, each an immature egg cell surrounded by follicle cells. The ovary makes the gametes and two steroid hormones: oestrogen from the growing follicle and progesterone from the corpus luteum. The ovary is not joined to the oviduct: at ovulation the egg is released into the body cavity and caught by the fimbriae of the oviduct (Fallopian tube), whose cilia and peristalsis carry it towards the uterus. Fertilisation normally happens in the upper third of the oviduct.
The uterus has three layers: the outer perimetrium, the thick smooth-muscle myometrium that contracts at birth, and the inner glandular endometrium, which thickens each cycle and is shed at menstruation. Its narrow lower end, the cervix, opens into the vagina, which receives semen and forms the birth canal.
| Male structure | Function | Female structure | Function |
|---|---|---|---|
| Seminiferous tubules | Make sperm; Sertoli cells nourish them | Ovarian follicles | Hold the oocyte; secrete oestrogen |
| Interstitial (Leydig) cells | Secrete testosterone | Corpus luteum | Secretes progesterone after ovulation |
| Epididymis | Maturation and storage of sperm | Oviduct (Fallopian tube) | Carries egg to uterus; site of fertilisation |
| Vas deferens | Carries sperm to the urethra | Uterus (endometrium) | Implantation and growth of the embryo |
| Seminal vesicles | Fructose, prostaglandins, alkaline fluid | Cervix | Neck between uterus and vagina |
| Prostate gland | Alkaline milky fluid; activates sperm | Vagina | Receives semen; birth canal |
| Cowper's glands | Lubricating mucus; neutralises urine |
Hormonal control in the male. From puberty, GnRH from the hypothalamus makes the anterior pituitary secrete FSH and LH. FSH acts on the seminiferous tubules (through the Sertoli cells) and promotes spermatogenesis. LH makes the interstitial cells secrete testosterone, which is needed for sperm production and brings on the secondary sexual characteristics. Testosterone feeds back to limit LH, and inhibin from the Sertoli cells limits FSH. This control is steady, not cyclic.
B8.1.2 Spermatogenesis and oogenesis
Both processes have three stages: multiplication by mitosis, growth, and maturation by meiosis, which halves the chromosome number from 46 (2n) to 23 (n). They differ in where and when they happen and in how many usable gametes result.
Spermatogenesis takes place in the wall of the seminiferous tubule, from the outer edge inwards to the lumen.
- Diploid spermatogonia (2n) at the edge divide repeatedly by mitosis, so the supply never runs out.
- Some grow into primary spermatocytes (2n).
- Each primary spermatocyte completes meiosis I to give two secondary spermatocytes (n).
- Each secondary spermatocyte completes meiosis II to give two spermatids (n): four from one primary spermatocyte.
- The round spermatids change shape without dividing into spermatozoa: a head with the nucleus and enzyme-filled acrosome, a middle piece packed with mitochondria, and a tail for swimming.
Spermatogenesis begins at puberty, is continuous for life, and all four products are functional gametes. Millions of sperm are made each day.
Oogenesis begins in the ovary of the female foetus and is spread over decades.
- Before birth, oogonia (2n) multiply by mitosis and grow into primary oocytes (2n), each enclosed in follicle cells. No new oogonia form after birth.
- The primary oocytes begin meiosis I but stop in prophase I. They stay arrested from before birth until, one by one, they are recruited in cycles after puberty; the rest stay arrested until menopause.
- In each cycle FSH makes a few follicles grow and usually one matures. Just before ovulation its primary oocyte completes meiosis I. The division is unequal: nearly all the cytoplasm goes to the secondary oocyte (n), almost none to the tiny first polar body (n).
- The secondary oocyte starts meiosis II but stops at metaphase II. This is the cell released at ovulation.
- Meiosis II is completed only if a sperm enters. Again unequal: a large ovum (n) and a tiny second polar body (n). The polar bodies degenerate.
So one primary oocyte gives one ovum and two or three polar bodies. The unequal divisions concentrate the stored food in one large gamete that must feed the embryo until implantation.
| Feature | Spermatogenesis | Oogenesis |
|---|---|---|
| Site | Seminiferous tubules of testis | Follicles of ovary |
| Begins | At puberty | Before birth |
| Ends | Continues through life | At menopause |
| Timing | Continuous | Arrested at prophase I (until the cycle) and metaphase II (until sperm entry) |
| Cytoplasm division | Equal | Unequal, with polar bodies |
| Gametes per primary cell | 4 sperm | 1 ovum (plus polar bodies) |
| Gamete | Small, motile, little cytoplasm | Large, non-motile, rich in cytoplasm |
Chromosome numbers to memorise. Spermatogonium 46, primary spermatocyte 46, secondary spermatocyte 23, spermatid and sperm 23. Oogonium 46, primary oocyte 46, secondary oocyte 23, polar bodies 23, ovum 23. Fertilisation restores 46. A "primary" spermatocyte or oocyte is still diploid: meiosis has not yet reduced the number.
MDCAT trap: ovulation does not release an ovum. The cell that leaves the ovary at ovulation is a secondary oocyte arrested at metaphase II, with its first polar body beside it. It becomes an ovum only after a sperm has entered and meiosis II has been completed. So "the cell released at ovulation" is the secondary oocyte, and meiosis II in the female is completed after sperm entry, not at ovulation. Two rules come with this one: the primary oocyte has been waiting in prophase I since before the girl was born, so "oogenesis begins at puberty" is wrong (ovulation begins at puberty); and the ovum and every polar body are haploid, so a polar body with 46 chromosomes is impossible.
Worked example. 120 primary spermatocytes and, over many years, 120 primary oocytes complete meiosis. How many functional gametes does each group produce, and how many chromosomes does each carry?
Step 1: each primary spermatocyte gives two secondary spermatocytes, then four spermatids, all of which become sperm: 120 × 4 = 480 sperm.
Step 2: each primary oocyte gives one secondary oocyte plus a polar body, and the secondary oocyte gives one ovum plus a polar body: 120 × 1 = 120 ova, with 240 to 360 polar bodies that degenerate.
Step 3: both gametes are haploid, 23 chromosomes, because meiosis I halved the diploid 46.
B8.2 Reproductive cycle and development
B8.2.1 The menstrual cycle and its hormonal control
From menarche (the first cycle, around 11 to 14 years) to menopause (around 45 to 55 years) the female body runs a cycle of about 28 days that prepares one egg and a uterine lining to receive it. Day 1 is the first day of bleeding. The cycle is really two linked cycles, one in the ovary and one in the uterus, run by four hormones: FSH and LH from the anterior pituitary (under GnRH from the hypothalamus), and oestrogen and progesterone from the ovary.
Menstrual phase (about days 1 to 5). Oestrogen and progesterone are at their lowest, so the thick endometrium breaks down and is shed with some blood. The low ovarian hormones release the pituitary from negative feedback, so FSH starts to rise.
Follicular, or proliferative, phase (about days 6 to 13). FSH makes several follicles grow; one becomes the dominant Graafian follicle and secretes rising amounts of oestrogen, which repairs and thickens the endometrium. At moderate levels oestrogen holds FSH and LH down by negative feedback, but when it peaks just before mid-cycle the feedback becomes positive: high oestrogen triggers a sudden surge of LH.
Ovulation (about day 14). The LH surge makes the primary oocyte finish meiosis I and ruptures the Graafian follicle, releasing the secondary oocyte into the oviduct. LH, not FSH, triggers ovulation. Body temperature rises slightly afterwards and stays raised for the rest of the cycle.
Luteal, or secretory, phase (about days 15 to 28). LH turns the empty follicle into the yellow corpus luteum, which secretes progesterone and some oestrogen. Progesterone makes the endometrium thick, spongy and secretory, and the two hormones together inhibit FSH and LH by negative feedback, so no new follicle develops. The corpus luteum lives about 14 days. If no embryo signals its presence it degenerates into the corpus albicans around day 26, progesterone and oestrogen fall sharply, the endometrium loses its support, and menstruation begins a new cycle. The luteal phase is the constant half of the cycle; the follicular phase is the part that varies.
| Hormone | Source | Peak | Main effects |
|---|---|---|---|
| FSH | Anterior pituitary | Early follicular phase | Growth of follicles; stimulates oestrogen secretion |
| Oestrogen | Growing follicle (later corpus luteum and placenta) | Just before ovulation | Rebuilds endometrium; at high level triggers the LH surge |
| LH | Anterior pituitary | Sharp surge at about day 14 | Ovulation; forms and maintains the corpus luteum |
| Progesterone | Corpus luteum (later placenta) | About day 21 | Maintains secretory endometrium; inhibits FSH and LH; its fall causes menstruation |
Contraceptive pill. The combined pill contains synthetic oestrogen and progesterone. Taken daily they keep the pituitary under constant negative feedback, so FSH and LH stay low, no follicle matures, there is no LH surge and no ovulation. The same feedback stops a second ovulation during a natural luteal phase and during pregnancy.
MDCAT trap: which hormone does what, and in which direction. Three mix-ups cost marks every year. First, ovulation is triggered by LH, not FSH: FSH grows the follicle, LH bursts it. Second, menstruation is caused by a fall, the drop in progesterone (and oestrogen) when the corpus luteum dies, not by a rise in any hormone; "menstruation is caused by a rise in FSH" has cause and effect reversed, because FSH rises as a result of the low ovarian hormones. Third, feedback changes direction: moderate oestrogen inhibits FSH and LH, the oestrogen peak before mid-cycle stimulates the LH surge, and progesterone is purely inhibitory. Keep the chain: FSH → follicle → oestrogen → LH surge → ovulation → corpus luteum → progesterone → (no fertilisation) progesterone falls → menstruation.
Worked example. A woman's cycles are regular but short, lasting 24 days. On about which day does she ovulate, and on which days could intercourse lead to pregnancy, given that sperm survive about 3 days in the female tract and the oocyte about 1 day?
Step 1: the luteal phase is fixed at about 14 days whatever the cycle length, because the corpus luteum lives about 14 days.
Step 2: ovulation day = cycle length − 14 = 24 − 14 = day 10. (Day 14 is right only for a 28-day cycle.)
Step 3: sperm present up to 3 days before ovulation can still fertilise, and the oocyte lasts about 1 day after, so the fertile window is about day 7 to day 11. For this woman it opens only two days after menstruation ends, so "no conception is possible soon after a period" is false for short cycles.
B8.2.2 Fertilisation, implantation, the placenta, stages of development, and sexually transmitted diseases
Fertilisation. Of the few hundred million sperm in an ejaculate only a few hundred reach the upper oviduct, where the secondary oocyte waits surrounded by follicle cells (corona radiata) and a glycoprotein coat (zona pellucida). When a sperm meets the oocyte its acrosome releases enzymes that digest a path through both layers (the acrosome reaction). The membranes fuse and the sperm nucleus enters. Entry sets off two events: the zona pellucida is altered so no second sperm can enter, and the oocyte completes meiosis II, releasing the second polar body. The haploid male and female nuclei then fuse: fertilisation is the fusion of nuclei, giving the diploid zygote (46 chromosomes). The sex of the child is fixed here by whether the sperm carried X or Y.
Cleavage and implantation. The zygote travels down the oviduct over about 3 to 4 days, dividing by mitosis as it goes. These divisions are cleavage: there is no growth between them, so the cells get smaller while the embryo stays the size of the zygote. 2 cells → 4 → 8 → a solid ball of 16 or more, the morula. Fluid collects inside and by about day 5 it is a hollow blastocyst: an outer layer, the trophoblast, which forms the membranes and the foetal part of the placenta, and an inner cell mass, which forms the embryo. About 6 to 7 days after fertilisation the trophoblast digests its way into the secretory endometrium: implantation.
Keeping the pregnancy. Implantation comes in the luteal phase, when the corpus luteum has only days left. The trophoblast secretes human chorionic gonadotrophin (hCG), which acts like LH and keeps the corpus luteum alive, so progesterone keeps rising and the endometrium is not shed: the first missed period. hCG passes into the urine, and its detection is the basis of the pregnancy test. By about the third month the placenta makes enough progesterone and oestrogen itself and the corpus luteum fades.
Germ layers. After implantation the inner cell mass forms three germ layers, and every organ comes from one of them.
| Germ layer | Gives rise to |
|---|---|
| Ectoderm (outer) | Epidermis of skin, hair and nails; whole nervous system; sense organs such as lens and retina; tooth enamel |
| Mesoderm (middle) | Muscle, bone and cartilage, dermis, blood and blood vessels, heart, kidneys, gonads, connective tissue |
| Endoderm (inner) | Lining of gut, lungs and bladder; liver, pancreas, thyroid and other glands that bud from the gut |
Membranes and placenta. The amnion encloses the amniotic fluid that cushions the embryo. The chorion, the outermost membrane, grows finger-like chorionic villi into the endometrium and forms the foetal part of the placenta; the maternal part is the endometrium itself. The villi are bathed in pools of maternal blood, but maternal and foetal blood never mix. Exchange is across the thin walls of the villi, mostly by diffusion: oxygen, glucose, amino acids, vitamins, salts and maternal antibodies (passive immunity) pass to the foetus; carbon dioxide and urea pass back. The barrier is not selective enough to stop alcohol, nicotine, many drugs and some viruses (rubella, HIV). The placenta is also an endocrine gland, secreting hCG, progesterone and oestrogen. The umbilical cord carries two umbilical arteries, taking deoxygenated blood from foetus to placenta, and one umbilical vein, returning oxygenated, nutrient-rich blood to the foetus: the reverse of the usual rule that arteries carry oxygenated blood.
Stages of development and birth. Gestation lasts about 266 days from fertilisation (about 280 days, 40 weeks, from the last period), in three trimesters. The developing human is an embryo from fertilisation to the end of the eighth week, when all the main organs are laid down (so this is when drugs and infections do the most damage), and a foetus from the ninth week to birth, a period mainly of growth. Birth is driven by oxytocin from the posterior pituitary, which contracts the myometrium; stretching of the cervix stimulates more oxytocin, a positive feedback loop that ends when the baby and then the placenta are delivered. Prolactin stimulates milk production and oxytocin causes its release during suckling.
Sexually transmitted diseases (STDs). These infections pass mainly through sexual contact; some also pass through blood, shared needles, or from mother to child during pregnancy or birth. Bacterial STDs can be cured with antibiotics if treated early; viral STDs can be controlled but not cured.
| Disease | Causative agent | Type | Key points |
|---|---|---|---|
| Gonorrhoea | Neisseria gonorrhoeae | Bacterium (diplococcus) | Discharge and painful urination; often symptomless in women; untreated, blocks oviducts or vas deferens and causes infertility; antibiotics cure it |
| Syphilis | Treponema pallidum | Bacterium (spirochaete) | Painless sore (chancre), then rash and fever, then years later damage to heart and brain; crosses the placenta; penicillin cures it |
| AIDS | Human immunodeficiency virus (HIV) | Retrovirus | Destroys helper T cells, so the body dies of opportunistic infections; spread by semen, blood, needles, mother to child; no cure, controlled by antiretroviral drugs |
| Genital herpes | Herpes simplex virus (mainly type 2) | DNA virus | Painful genital blisters; the virus hides in nerve cells and sores return; no cure; can infect the baby at birth |
MDCAT trap: where things happen and which way blood flows. Fertilisation happens in the oviduct, not the uterus or ovary; the uterus is where implantation happens, and the stage that implants is the blastocyst, not the zygote or morula. Cleavage is mitosis (the zygote is already diploid, so there is nothing to halve), and because there is no growth between divisions the cells get smaller, not the embryo bigger. In the placenta the two blood supplies lie close but do not mix: the foetus gets oxygen by diffusion, not by receiving maternal blood. The umbilical arteries carry deoxygenated blood away from the foetus and the single umbilical vein carries oxygenated blood to it. Finally, hCG comes from the embryo (its trophoblast), not from the mother's pituitary or ovary, and its job is to keep the corpus luteum, and so progesterone, going.
Worked example. A woman with a regular 28-day cycle has a positive urine pregnancy test on day 30, two days after her period was due. Explain, hormone by hormone, why her period did not come, and name the cell layer responsible.
Step 1: she ovulated about day 14 and fertilisation took place in the oviduct within a day. Cleavage produced a blastocyst that implanted around day 20 to 21.
Step 2: the trophoblast of the blastocyst began secreting hCG, which mimics LH and rescues the corpus luteum that would otherwise have degenerated around day 26.
Step 3: the surviving corpus luteum keeps secreting progesterone, so the secretory endometrium is maintained instead of shed, and FSH and LH stay suppressed so no further ovulation occurs.
Step 4: hCG is excreted in the urine, which is what the test detects. Later the placenta takes over progesterone production.
Practice MCQs
- Testosterone is secreted by the:
A. Sertoli cells of the seminiferous tubules
B. epithelium of the epididymis
C. interstitial cells between the seminiferous tubules
D. prostate gland - The cell released from the human ovary at ovulation is a:
A. primary oocyte arrested in prophase I
B. secondary oocyte arrested in metaphase II
C. mature ovum that has completed meiosis
D. diploid oogonium - In a sample of testis tissue, 30 secondary spermatocytes complete meiosis. The number of sperm formed, and the number of chromosomes in each, will be:
A. 30 sperm, 23 chromosomes
B. 120 sperm, 23 chromosomes
C. 60 sperm, 46 chromosomes
D. 60 sperm, 23 chromosomes - A man's semen contains normal numbers of motile sperm but almost no fructose. The gland most likely to be defective is the:
A. seminal vesicle
B. prostate gland
C. Cowper's gland
D. epididymis - Menstruation begins at the end of a cycle because:
A. the pituitary suddenly releases a surge of LH
B. rising oestrogen from the new follicle breaks down the endometrium
C. FSH stimulates the uterus to contract
D. the corpus luteum degenerates and progesterone falls - A woman has regular cycles of 35 days. On about which day of her cycle does ovulation occur?
A. Day 14
B. Day 21
C. Day 17
D. Day 28 - The combined contraceptive pill prevents pregnancy mainly by:
A. keeping FSH and LH low so that no follicle matures and no ovulation occurs
B. stimulating the LH surge so that ovulation happens before the lining is ready
C. preventing the corpus luteum from forming after ovulation
D. destroying sperm in the vagina - Human chorionic gonadotrophin (hCG) is secreted by the:
A. corpus luteum, to maintain the trophoblast
B. anterior pituitary, to trigger implantation
C. trophoblast of the embryo, to maintain the corpus luteum
D. endometrium, to stimulate cleavage - Syphilis is caused by:
A. Treponema pallidum
B. Neisseria gonorrhoeae
C. herpes simplex virus
D. human immunodeficiency virus - A blood sample is taken from an umbilical artery of a foetus. Compared with blood in the umbilical vein, it will have:
A. more oxygen and less carbon dioxide, because it is arterial blood
B. the same composition, because maternal and foetal blood mix in the placenta
C. more glucose, because it has just left the placenta
D. less oxygen and more carbon dioxide, because it is flowing from the foetus to the placenta
1. C. Testosterone comes from the interstitial (Leydig) cells between the tubules; Sertoli cells nourish sperm and secrete inhibin, not testosterone.
2. B. Meiosis I finishes just before ovulation, so the released cell is a secondary oocyte held at metaphase II; it becomes an ovum only after sperm entry.
3. D. Each secondary spermatocyte is already haploid and divides once more (meiosis II) into two spermatids, so 30 × 2 = 60 sperm, each with 23 chromosomes.
4. A. Fructose, the energy source of sperm, is the secretion of the seminal vesicles; the prostate and Cowper's glands add alkaline and lubricating fluids.
5. D. The corpus luteum lives about 14 days; when it degenerates, progesterone falls and the unsupported endometrium is shed. Menstruation is caused by a fall, not a rise.
6. B. The luteal phase is fixed at about 14 days, so ovulation is 14 days before the next period: 35 − 14 = day 21.
7. A. The synthetic oestrogen and progesterone in the pill exert constant negative feedback on the pituitary, so FSH and LH stay low and no follicle develops or ruptures.
8. C. hCG is made by the trophoblast of the implanted blastocyst; it acts like LH and rescues the corpus luteum so progesterone continues and the endometrium is kept.
9. A. Treponema pallidum, a spirochaete bacterium, causes syphilis; Neisseria gonorrhoeae causes gonorrhoea, and the two viruses cause genital herpes and AIDS.
10. D. The two umbilical arteries carry deoxygenated, waste-laden blood from the foetus to the placenta; the single umbilical vein brings oxygenated, glucose-rich blood back. The circulations never mix.
Before the test: 12 facts to recite
- Seminiferous tubules make sperm; interstitial (Leydig) cells make testosterone; Sertoli cells nourish sperm.
- Sperm route: seminiferous tubule → epididymis (maturation and storage) → vas deferens → ejaculatory duct → urethra.
- Seminal vesicles give fructose and prostaglandins; prostate gives alkaline milky fluid; Cowper's glands give lubricating mucus.
- In the male, FSH drives spermatogenesis and LH drives testosterone secretion.
- One primary spermatocyte → 4 sperm; one primary oocyte → 1 ovum plus polar bodies; all gametes have 23 chromosomes.
- Primary oocytes wait in prophase I from before birth; the cell ovulated is a secondary oocyte in metaphase II; meiosis II finishes only after sperm entry.
- Cycle order: menstruation (days 1 to 5) → FSH and follicle growth → oestrogen → LH surge and ovulation (day 14) → corpus luteum and progesterone.
- LH triggers ovulation; the fall in progesterone when the corpus luteum dies triggers menstruation; the luteal phase is always about 14 days.
- Oestrogen and progesterone inhibit FSH and LH by negative feedback, which is how the pill prevents ovulation.
- Fertilisation is in the oviduct; cleavage is mitosis without growth: zygote → morula → blastocyst, which implants in the endometrium about 6 to 7 days after fertilisation.
- hCG from the trophoblast keeps the corpus luteum alive; maternal and foetal blood do not mix; two umbilical arteries carry deoxygenated blood, one vein carries oxygenated blood.
- Ectoderm → skin and nervous system; mesoderm → muscle, bone, blood, heart; endoderm → gut and lung linings. Gonorrhoea: Neisseria gonorrhoeae; syphilis: Treponema pallidum; AIDS: HIV; genital herpes: herpes simplex virus.
